ダクラタスビル
ダクラタスビル(英:Daclatasvir)は、経口C型肝炎治療薬の一つである。アスナプレビルと併用する事で、注射を要しないC型肝炎の治療が可能となった。第一世代の直接作用型抗ウイルス薬とされる。商品名はダクルインザである。開発コードはBMS-790052である。WHO必須医薬品モデル・リストに収載されている[1]。
| ダクラタスビル | |
|---|---|
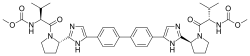 | |
Methyl [(2S)-1-{(2S)-2-[4-(4’-{2-[(2S)-1-{(2S)-2-[(methoxycarbonyl)amino]-3-methylbutanoyl}-2-pyrrolidinyl]-1H-imidazol-4-yl}-4-biphenylyl)-1H-imidazol-2-yl]-1-pyrrolidinyl}-3-methyl-1-oxo-2-butanyl]carbamate | |
別称 BMS-790052 | |
| 識別情報 | |
| CAS登録番号 | 1009119-64-5  |
| ChemSpider | 24609522 |
| KEGG | D10065 |
| ChEBI | |
| ChEMBL | CHEMBL2023898 |
| ATC分類 | J05AX14 |
| |
| |
| 特性 | |
| 化学式 | C40H50N8O6 |
| モル質量 | 738.88 g mol−1 |
| 特記なき場合、データは常温 (25 °C)・常圧 (100 kPa) におけるものである。 | |
承認状況
日本では2014年7月にアスナプレビルと併用することを条件に同時に承認された[2]。
欧州では2014年8月にソホスブビルと併用することを条件に承認された[3]。
米国では承認申請が断念された[4]。また日本でも2021年に販売が中止された。
効能・効果
セログループ1(ジェノタイプ1)のC型慢性肝炎またはC型代償性肝硬変におけるウイルス血症の改善
禁忌
次の患者には禁忌である。
- 製剤成分に過敏症のある患者
- リファンピシン、リファブチン、フェニトイン、カルバマゼピン、フェノバルビタール、デキサメタゾンを投与中の患者
- セイヨウオトギリソウ(セント・ジョーンズ・ワート)含有食品を摂取している患者
慎重投与
- B型肝炎罹患者または既往者では、B型肝炎ウイルスが再活性化する可能性がある。
副作用
重大な副作用として知られているものには、肝機能障害(ALT(GPT)増加(8.6%)、AST(GOT)増加(5.6%)、血中ビリルビン増加(0.5%)、プロトロンビン時間延長、アルブミン低下)、肝不全、多形紅斑、血小板減少、間質性肺炎がある[5]。
5%以上の患者に、好酸球増加症、発熱、倦怠感、頭痛、ALT(GPT)増加、AST(GOT)増加が出現する。
作用機序
ダクラタスビルはC型肝炎ウイルス(HCV)のNS5Aを阻害する[6][7]。近年の研究では、ウイルス複製過程の2箇所を阻害してHCV RNAを速やかに減少させるとされている[8]。
ダクラタスビルについては、アスナプレビル[9][10][11][12]やソホスブビル[13][14]といった直接作用型抗ウイルス薬と同様、ペグ化インターフェロンやリバビリンとの併用効果が臨床試験で確認された[15]
出典
- “www.who.int”. 2015年5月11日閲覧。
- “日本初のインターフェロンおよびリバビリンを必要としない経口薬のみによるC型慢性肝炎の治療薬 世界に先駆けて日本で製造販売承認を取得”. ブリストル・マイヤーズ (2014年7月4日). 2015年5月11日閲覧。
- “ブリストル「ダクルインザ」、欧州でC型肝炎併用療法の承認取得”. The Wall Street Journal (2014年8月27日). 2015年5月11日閲覧。
- “ブリストル、C型肝炎の併用療法の米国承認申請を断念”. The Wall Street Journal (2014年10月8日). 2015年5月11日閲覧。
- “ダクルインザ錠60mg 添付文書” (2016年5月). 2016年7月1日閲覧。
- Gao, Min; Nettles, Richard E.; Belema, Makonen; Snyder, Lawrence B.; Nguyen, Van N.; Fridell, Robert A.; Serrano-Wu, Michael H.; Langley, David R.; Sun, Jin-Hua; O'Boyle, Donald R., II; Lemm, Julie A.; Wang, Chunfu; Knipe, Jay O.; Chien, Caly; Colonno, Richard J.; Grasela, Dennis M.; Meanwell, Nicholas A.; Hamann, Lawrence G. (2010). “Chemical genetics strategy identifies an HCV NS5A inhibitor with a potent clinical effect”. Nature 465 (7294): 96–100. doi:10.1038/nature08960. PMID 20410884.
- Bell, Thomas W. (2010). “Drugs for hepatitis C: unlocking a new mechanism of action”. ChemMedChem 5 (10): 1663–1665. doi:10.1002/cmdc.201000334. PMID 20821796.
- Guedj, J et al. (2013-02-19). “Modeling shows that the NS5A inhibitor daclatasvir has two modes of action and yields a shorter estimate of the hepatitis C virus half-life.”. Proceedings of the National Academy of Sciences. 2015年5月11日閲覧。.
- Preliminary Study of Two Antiviral Agents for Hepatitis C Genotype 1. Lok, A et al. New England Journal of Medicine. 366(3):216-224. January 19, 2012.
- “Bristol-Myers' Daclatasvir, Asunaprevir Cured 77%: Study”. Bloomberg (2012年4月19日). 2015年5月11日閲覧。
- AASLD: Daclatasvir plus Asunaprevir Rapidly Suppresses HCV in Prior Null Responders. Highleyman, L. HIVandHepatitis.com. 8 November 2011.
- High rate of response to BMS HCV drugs in harder-to-treat patients – but interferon-free prospects differ by sub-genotype. Alcorn, K. Aidsmap.com. 12 November 2012.
- AASLD 2012: Sofosbuvir + Daclatasvir Dual Regimen Cures Most Patients with HCV Genotypes 1, 2, or 3. Highleyman, L. HIVandHepatitis.com. 15 November 2012.
- Mark Sulkowski et al. (January 16, 2014). “Daclatasvir plus Sofosbuvir for Previously Treated or Untreated Chronic HCV Infection”. New England Journal of Medicine. doi:10.1056/NEJMoa1306218.
- AASLD: Daclatasvir with Pegylated Interferon/Ribavirin Produces High Rates of HCV Suppression. Highleyman, L. HIVandHepatitis.com. 6 December 2011.